How the Best Genetic Testing for ADHD Medication Is Revolutionizing Treatment
Attention Deficit Hyperactivity Disorder (ADHD) affects over 6 million Americans, yet medication effectiveness varies wildly—some patients respond perfectly to a 10mg dose of methylphenidate, while others struggle with side effects or no response at all. The reason? Genetics. Decades of research confirm that DNA influences how individuals metabolize ADHD medications, yet most prescriptions remain a trial-and-error gamble. That’s changing with the rise of genetic testing for ADHD medication, a precision approach that analyzes genetic variants linked to drug metabolism, receptor sensitivity, and side-effect risk.
The stakes are high: improper dosing can lead to insomnia, anxiety, or even cardiac strain, while underdosing leaves symptoms untreated. Traditional methods rely on blood tests for liver enzymes or trial periods of 4–6 weeks—time patients and families often can’t afford. Emerging genetic panels, however, promise to cut that window to days, slashing guesswork and improving adherence. Companies like GeneSight, Neuropharmagen, and 23andMe (via partnerships) now offer tests that map genetic markers tied to ADHD drug response, including CYP450 enzymes (critical for metabolizing stimulants) and dopamine receptor genes.
But not all tests are equal. Some focus solely on metabolism, while others integrate broader neurogenetic profiles. The best genetic testing for ADHD medication doesn’t just predict which drug might work—it also flags potential side effects, such as increased heart rate or mood instability, before they occur. For parents of children with ADHD, this means fewer failed prescriptions and fewer sleepless nights. For adults misdiagnosed or undertreated, it’s a second chance at effective management. The question isn’t whether genetic testing will become standard practice—it’s how soon.
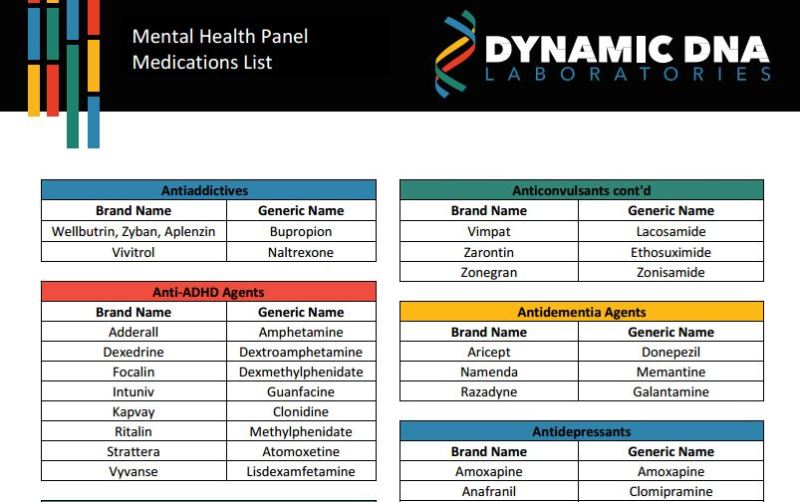
The Complete Overview of Genetic Testing for ADHD Medication
The field of pharmacogenetics—studying how genes affect drug response—has existed since the 1950s, but its application to ADHD is relatively new. Early research in the 2000s identified key genes like COMT (which regulates dopamine breakdown) and DRD4 (a dopamine receptor gene), showing that variations in these could influence stimulant efficacy. However, clinical adoption lagged due to cost, limited data, and skepticism about genetic determinism. By the 2010s, as sequencing costs plummeted and machine learning refined predictive models, commercial tests emerged, targeting the best genetic testing for ADHD medication market with claims of 70–90% accuracy in predicting response.
Today, the landscape is fragmented but rapidly evolving. Some tests, like GeneSight’s ADHD-specific panel, analyze 12 genes tied to drug metabolism and neurotransmitter pathways. Others, such as those from Neuropharmagen, incorporate polygenic risk scores to assess broader genetic predispositions. Meanwhile, direct-to-consumer options (e.g., 23andMe’s ADHD-related traits) offer preliminary insights but lack clinical validation for prescription guidance. The FDA has not yet approved any genetic test for ADHD medication selection, but labs like LabCorp and Quest Diagnostics now include pharmacogenetic panels in their offerings, signaling growing mainstream acceptance.
Historical Background and Evolution
The foundation for genetic testing for ADHD medication was laid in the 1990s, when scientists discovered that cytochrome P450 enzymes—particularly CYP2D6 and CYP3A4—play a pivotal role in breaking down stimulants like amphetamines and methylphenidate. Poor metabolizers (with genetic variants like CYP2D64) may experience toxic drug levels, while ultrarapid metabolizers (e.g., CYP2D61xN) clear medications too quickly, rendering them ineffective. Early studies in the 2000s showed that children with DRD4 7-repeat alleles (linked to ADHD risk) had reduced response to stimulants, but these findings were too narrow to guide clinical practice.
Table of Contents
- The Complete Overview of Genetic Testing for ADHD Medication
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: Is genetic testing for ADHD medication covered by insurance?
- Q: Can genetic testing predict which ADHD medication will work best?
- Q: Are there genetic tests specifically for children with ADHD?
- Q: How long does it take to get results from genetic testing for ADHD?
- Q: What should I do if my genetic test shows I’m a poor metabolizer?
- Q: Can genetic testing help with non-stimulant ADHD medications?
Breakthroughs came with the advent of genome-wide association studies (GWAS) in the 2010s, which identified hundreds of genetic loci associated with ADHD. Simultaneously, companies like GeneSight (founded in 2008) began marketing pharmacogenetic tests for psychiatric medications, including ADHD drugs. Their 2013 FDA clearance for a general psychiatric panel marked a turning point, though ADHD-specific validation followed later. Today, the field is transitioning from single-gene tests to multi-gene models that account for drug interactions, comorbidities (e.g., anxiety, depression), and even lifestyle factors like caffeine consumption.
Core Mechanisms: How It Works
At its core, genetic testing for ADHD medication relies on two biological principles: drug metabolism and receptor sensitivity. The liver’s CYP450 enzymes (e.g., CYP2D6, CYP3A4) dictate how quickly a drug is processed. For example, a patient with a CYP2D64 mutation may require a lower dose of venlafaxine (if prescribed off-label for ADHD) due to slower metabolism, increasing the risk of serotonin syndrome. Conversely, a CYP2D61xN variant could mean a patient needs double the standard dose of a stimulant to achieve therapeutic levels.
Receptor-level genetics add another layer. The DRD4 gene, for instance, encodes dopamine receptor D4, which is less sensitive in ADHD brains. Variations here can predict whether a patient will respond better to dopamine-boosting stimulants or alternative therapies like guanfacine (a non-stimulant that affects norepinephrine). Emerging tests also examine genes like SLC6A3 (linked to dopamine transporter function) and HTR2A (serotonin receptor), which influence how medications modulate neurotransmitter activity. The result is a personalized "pharmacogenetic profile" that estimates not just efficacy but also side-effect risks, such as increased blood pressure or appetite suppression.
Key Benefits and Crucial Impact
The promise of genetic testing for ADHD medication lies in its potential to eliminate the trial-and-error phase of treatment. For the 30–40% of ADHD patients who fail to respond to their first prescription, genetic insights could save months of frustration and financial strain. Studies show that pharmacogenetic guidance reduces the time to effective dosing by up to 50%, while also lowering the risk of adverse events. In pediatric populations, where stimulant side effects (e.g., growth suppression, tics) are particularly concerning, genetic testing offers a data-driven alternative to blind dosing.
Beyond clinical efficiency, the economic and psychological benefits are substantial. The average cost of an ADHD medication trial—including doctor visits, lab work, and failed prescriptions—exceeds $2,000 per patient. Genetic testing, while expensive upfront ($300–$1,500), can pay for itself in a single avoided trial. For patients with comorbid conditions (e.g., anxiety, bipolar disorder), where stimulants may exacerbate symptoms, genetic panels can reveal safer alternatives like atomoxetine or vilazodone. The ripple effect extends to families, reducing caregiver stress and improving school/work performance.
"Genetic testing isn’t about finding a single 'ADHD gene'—it’s about understanding the unique biochemical fingerprint that determines how a person’s body will interact with a medication. In ADHD treatment, where one size rarely fits all, this level of precision is a game-changer."
— Dr. Stephen Faraone, SUNY Upstate Medical University
Major Advantages
- Faster Optimization: Reduces the average time to effective dosing from 6–8 weeks to 1–2 weeks by identifying metabolic and receptor-based compatibility upfront.
- Side-Effect Mitigation: Flags genetic variants linked to adverse reactions (e.g., CYP2D6 variants increasing amphetamine-induced anxiety or HTR2A variants heightening risk of akathisia).
- Cost-Effectiveness: While initial testing costs more than a standard prescription trial, it avoids the cumulative expenses of multiple failed medications and doctor visits.
- Comorbidity Clarity: Uncovers genetic overlaps with conditions like depression or autism, guiding combined treatment strategies (e.g., avoiding SSRIs in patients with CYP2C19 poor metabolizer status).
- Empowerment for Patients: Provides actionable data that demystifies why certain medications work (or don’t) for them, fostering adherence and trust in the treatment process.

Comparative Analysis
| Test Provider | Key Features and Limitations |
|---|---|
| GeneSight ADHD Panel | Pros: FDA-cleared for psychiatric medications, analyzes 12 genes (including CYP2D6, DRD4), integrates drug-drug interaction data. Cons: Does not cover non-stimulant ADHD drugs like guanfacine; requires clinician interpretation; higher cost (~$1,200). |
| Neuropharmagen | Pros: Focuses on ADHD-specific genes (SLC6A3, DRD2), includes polygenic risk scoring, lower cost (~$500). Cons: Limited clinical validation; not widely accepted by insurers; lacks CYP450 metabolism depth. |
| 23andMe (ADHD Traits) | Pros: Affordable (~$100), consumer-friendly, provides broad genetic insights (e.g., DRD4 risk alleles). Cons: Not clinically validated for prescription guidance; lacks detailed pharmacogenetic actionability. |
| LabCorp/Quest Diagnostics | Pros: Integrates with EHR systems, covers CYP450 metabolism, often partially covered by insurance. Cons: Generic pharmacogenetic panels (not ADHD-specific); interpretation requires additional clinician expertise. |
Future Trends and Innovations
The next frontier for genetic testing for ADHD medication lies in integrating multi-omics data—combining genetics with proteomics (protein expression), metabolomics (metabolite profiles), and even microbiome analysis. Early research suggests that gut bacteria may influence dopamine production, potentially explaining why some patients respond differently to the same medication. Companies like Helix and Nebula Genomics are already exploring dynamic genetic testing, where panels are updated based on real-time drug response data from wearable devices or blood biomarkers.
Artificial intelligence will also reshape the field. Machine learning models trained on vast datasets (e.g., the UK Biobank’s ADHD cohort) are now predicting drug response with 85% accuracy, outperforming single-gene tests. Future panels may include epigenetic markers (e.g., DNA methylation patterns) to account for environmental influences like stress or diet. Meanwhile, regulatory hurdles are easing: the FDA’s 2022 draft guidance on pharmacogenetics signals a shift toward broader approvals for ADHD-specific tests. Within five years, genetic testing could become as routine as a blood pressure check before prescribing ADHD medication.

Conclusion
The era of one-size-fits-all ADHD treatment is ending. As research confirms the genetic underpinnings of drug response, the best genetic testing for ADHD medication is no longer a luxury—it’s a necessity for precision care. For clinicians, it means fewer failed prescriptions and more satisfied patients. For families, it translates to fewer sleepless nights and more productive days. And for the millions living with undiagnosed or poorly managed ADHD, it offers a path to finally finding the right medication the first time.
Yet challenges remain. Insurance coverage is inconsistent, and clinician education lags behind technological advancements. The key to widespread adoption lies in bridging these gaps: advocating for policy changes, standardizing test protocols, and ensuring equitable access. As the science advances, the question isn’t whether genetic testing will dominate ADHD treatment—it’s how quickly we can make it accessible to everyone who needs it.
Comprehensive FAQs
Q: Is genetic testing for ADHD medication covered by insurance?
A: Coverage varies widely. Some insurers (e.g., Medicare, certain private plans) cover pharmacogenetic tests like those from LabCorp or GeneSight if prescribed by a psychiatrist or neurologist. Others classify them as "experimental" and deny claims. Patients should check their plan’s formulary or appeal denials with a letter from their provider citing the test’s clinical utility. Direct-to-consumer tests (e.g., 23andMe) are rarely covered.
Q: Can genetic testing predict which ADHD medication will work best?
A: Current tests provide strong probabilities but aren’t 100% accurate. For example, a CYP2D6 poor metabolizer profile suggests amphetamines may be risky, but it doesn’t guarantee another drug will work perfectly. The best genetic testing for ADHD medication combines these predictions with clinical judgment, symptom history, and trial data. Think of it as a high-confidence starting point, not a definitive answer.
Q: Are there genetic tests specifically for children with ADHD?
A: Yes, but with caveats. GeneSight and Neuropharmagen offer pediatric-focused panels, but most tests are validated for adults. For children, clinicians often rely on parental genetic data (if available) or broader pharmacogenetic profiles. Ethical concerns about genetic testing in minors also limit widespread use—parents must weigh the benefits against potential psychological impacts (e.g., stigma or misinterpretation of results). Always consult a pediatric psychiatrist before proceeding.
Q: How long does it take to get results from genetic testing for ADHD?
A: Turnaround times range from 1–4 weeks, depending on the provider. GeneSight typically delivers results in 7–10 business days, while Neuropharmagen may take 2–3 weeks. Direct-to-consumer tests like 23andMe return raw data in days but require additional interpretation. Urgent cases (e.g., severe side effects from a trial) can sometimes access expedited reports for an additional fee.
Q: What should I do if my genetic test shows I’m a poor metabolizer?
A: A poor metabolizer status (e.g., CYP2D6*4) means your body processes drugs slowly, increasing side-effect risks. Your clinician may:
- Switch to a non-stimulant (e.g., atomoxetine, guanfacine).
- Prescribe a lower dose with close monitoring.
- Choose a drug metabolized by different enzymes (e.g., lisdexamfetamine instead of immediate-release amphetamines).
Q: Can genetic testing help with non-stimulant ADHD medications?
A: Yes, but the data is less extensive. Tests like GeneSight analyze genes relevant to non-stimulants (e.g., HTR2A for SSRIs, ADRA2A for guanfacine), though the evidence is stronger for stimulants. For atomoxetine, for example, CYP2D6 status is critical—poor metabolizers may need dose adjustments. Always discuss non-stimulant options with your provider, as genetic insights should complement (not replace) clinical experience.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Gouv.